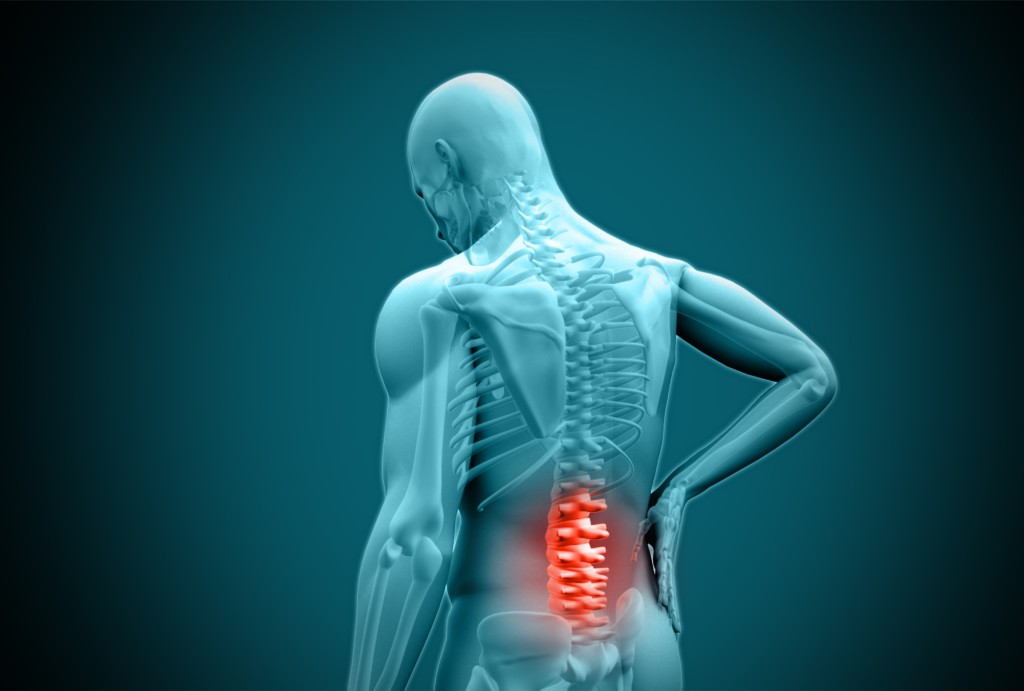


Spondylolisthesis means one of the bones in your lower back has slipped forward over the bone beneath it. Doctors often call it a slipped vertebra, and for most people it feels like low back pain that builds when you stand or walk and eases when you sit. Most slips are small, few get worse over time, and surgery is rarely part of the plan.
You may have first seen the word on an ER report after a car accident, or heard it from a doctor who was looking at something else. The grade next to it matters more than the diagnosis, because the grade tells you how far the bone has moved. Your grade, your spondylolisthesis symptoms, and the results of a hands-on exam decide what happens next, and for most people that means treatment without surgery.
What Is Spondylolisthesis?
Your spine is a stack of bones called vertebrae. Each one is held in place by a disc at the front and a pair of small joints at the back. When those supports loosen, the bone can slide forward over the one below it. The slip almost always happens low in the back, at the last lumbar bone (L5) over the top of the tailbone (S1), or one level up at L4 over L5. Those two levels carry the most weight and sit at the sharpest angle.
Spondylolysis, a similar word that often appears on the same report, is a crack in the pars interarticularis, the thin bridge of bone at the back of the vertebra. Spondylolisthesis is the slide itself. You can have the crack for years without any slip, and you can have a slip without a crack.
Many people have a slip and never feel it. It shows up on an X-ray taken for something else, and finding out you have carried one for ten years is one of the most common ways people learn about it.
Spondylolisthesis Symptoms to Watch For
Spondylolisthesis symptoms come from the bone moving and from pressure the slip puts on the nerves running past it.
- Low back pain that gets worse when you stand, walk, or lean backward
- Relief when you sit, lean forward, or lie down
- Tight hamstrings, often the first sign a physical therapist notices
- Pain, numbness, or tingling that runs from your buttock into your thigh
- A leg or foot that feels weak or gives way
- A change in how you stand or walk, with your pelvis tilting to compensate
- Neurogenic claudication, leg pain or heaviness that builds the longer you walk and eases once you sit down, a sign the nerves are being squeezed
A slip caused by age-related wear often narrows the spinal canal as it goes, and lumbar stenosis frequently appears on the same report for that reason.
The size of the slip does not predict how much it hurts. A grade 1 slip can cause daily pain while a grade 3 causes none, and a slip that never bothered you can start hurting after a car accident or a fall without looking any different on the X-ray. A hands-on exam sorts out what the film cannot, and your visit starts there.
Grade 1 vs Grade 2 Spondylolisthesis: What the Grades Mean
Doctors measure a slip with the Meyerding scale, which divides the top of the lower vertebra into quarters and records how many of them the upper bone has crossed.
| Grade | How far the bone has slipped | What it means for you |
| Grade 1 | Up to 25% | Low grade, usually stable, treated without surgery |
| Grade 2 | 25 to 50% | Low grade, still treated conservatively first |
| Grade 3 | 50 to 75% | High grade, higher chance of nerve pressure |
| Grade 4 | 75 to 100% | High grade, surgery is often discussed |
| Grade 5 | Over 100% | Spondyloptosis, the bone has dropped off the one below |
Grade 1 spondylolisthesis is by far the most common finding. At that stage the segment is usually stable, symptoms respond to conservative care, and the odds of it getting worse are low in adults. A grade 1 on your report is not a countdown to surgery.
Grades 1 and 2 together make up the large majority of cases. Grade 3 and above change the conversation, since the risk of nerve pressure rises with the distance and high-grade slips are more often the type that started with a fracture.
What Causes Spondylolisthesis?
A Stress Fracture From Sports
Isthmic spondylolisthesis starts with a stress fracture in the pars interarticularis. Repeated arching of the lower back breaks it, and the crack turns up in gymnasts, divers, football linemen, and volleyball players, usually during a growth spurt. The fracture happens young, the slip may not follow for years, and many adults learn about both at the same time.
Age and Wear on the Spine
Degenerative spondylolisthesis needs no fracture. Discs lose height, the facet joints at the back of the spine wear down, and eventually nothing holds the segment where it belongs. It shows up after 50, is more common in women, and settles at L4 over L5. It travels with the same wear that causes degenerative disc disease, since both come from one process.
Injury and Other Causes
A vertebra can also slip after a hard fall, a work injury, or a car accident that fractures the bone holding it in place. An accident can also worsen a slip that was already there and had never caused trouble. Less often, the cause is a spine shape you were born with, a disease that weakens bone such as osteoporosis or a tumor, or a previous spine surgery that removed too much of the supporting structure.
How AICA Atlanta Diagnoses Spondylolisthesis

Standing X-Rays and Motion X-Rays
A side-view X-ray taken while you stand confirms the slip and gives it a grade, and the standing position is what makes the film accurate. A slip can settle back when you lie down, and a film taken lying flat in an emergency room can read smaller than the slip you stand and walk on all day.
Every AICA Atlanta clinic has X-ray on site, and our chiropractors take those views standing. When the question is whether the segment shifts when you move, we can use motion X-ray, a real-time image that watches the bone while you bend forward and back. A segment that slides between positions is unstable, and instability changes your treatment plan more than the grade alone does.
MRI shows what the bone is doing to the soft tissue around it, including whether a nerve is pinched and how much room the nerves have. Our clinics have access to an open MRI when leg symptoms call for it. A CT scan gives a close look at the bone itself when a fracture is suspected and the X-ray cannot settle it.
What the Exam Tells Us
Expect a neurological exam alongside the imaging. Your doctor will test your reflexes, your leg strength, and the feeling in your legs and feet. Those findings show whether the nerves are affected, and they matter more for your treatment plan than the percentage on the report.
Spondylolisthesis Treatment Without Surgery
Conservative care is the first step for grade 1 and grade 2 slips, and few people ever need to move past it.
Building Support Around the Slip
Strong deep core and abdominal muscles give the segment the support the bone structures no longer provide. Exercises that bend you forward are usually easier on a slip than exercises that arch you back, because arching closes the space the nerves need. Loosening tight hamstrings and hip flexors takes some of the pull off the pelvis, and hamstring tightness is often the first thing to ease.
Chiropractic care for a slip works on the segments above and below the slipped one, not on the unstable level itself. An adjustment does not move the bone back. Restoring motion where the spine has stiffened reduces how much the affected level has to absorb. At AICA Atlanta your chiropractor, medical doctors, and physical therapist work in the same clinic, and the level that gets left alone is agreed on before care starts.
Easing Pain and Nerve Pressure
Pain relief starts with pausing the arching movements that aggravate the slip, breaking up long periods of standing, and adjusting how you lift. Anti-inflammatory medication helps during flares. Epidural steroid injections are an option when leg symptoms take over and are not settling.
Traction-based spinal decompression eases pressure on the discs and nerve roots, and your provider will want to evaluate you before starting it. The segment is already loose, and traction loads it differently than it loads a plain disc problem.
A brace helps a young athlete with a fresh stress fracture, where the goal is letting the bone heal. In an adult with a long-standing slip, wearing a brace for weeks weakens the muscles you are trying to build.
When Surgery Comes Up
Surgery becomes reasonable when nerve symptoms keep getting worse, when imaging confirms the segment is unstable, or when pain has not responded to several months of consistent conservative care. It is nobody’s first move for a grade 1 slip, and it helps to understand when back surgery is not the answer before anyone puts a date on the calendar.
Living With Spondylolisthesis Day to Day
Plenty of people carry a low-grade slip for decades without it running their lives, and a few habits keep it that way.
Standing, Lifting, and Work
Long stretches of standing aggravate a slip more than sitting does, and the fix is to break up anything that keeps you upright and still. When you have to stand in place, rest one foot on a low step or rail. That flattens your lower back slightly and takes load off the segment. Lift from a squat with the object close to your body, and skip the twist at the end.
Exercise That Helps and Exercise to Skip
Walking, swimming, and stationary cycling are usually well tolerated. Most strength work is too, as long as you keep your lower back out of an arch. What tends to flare a slip is repeated arching, including overhead pressing, running on hard surfaces without building up to it, and anything gymnastic.
When to Get Re-Checked
Book a visit sooner if leg symptoms start or spread, if you can walk a shorter distance before the pain sets in, or if you notice weakness anywhere in your leg or foot. Losing control of your bladder or bowels along with back pain is an emergency. Go to the emergency room.
Get Your Spondylolisthesis Evaluated at AICA Atlanta
A report naming a slipped vertebra tells you very little about what happens next. The grade, whether the segment is stable, and whether nerves are involved decide that. All three come from an exam and the right X-rays, and at AICA Atlanta they come from one visit. Our chiropractors, medical doctors, and physical therapists share one clinic with imaging on site, and a question about your back pain does not have to turn into three appointments across town. Grade 1 and grade 2 patients start in conservative care and most stay there. Find the AICA Atlanta clinic nearest you across our 20 Metro Atlanta locations and book a free consultation, or call 404.889.8828 at any hour. Same-day appointments are available, and we can arrange transportation if you cannot drive.
Frequently Asked Questions
Is grade 1 spondylolisthesis serious?
Rarely. It is the mildest category, the segment is usually stable, and conservative treatment handles most cases. It seldom gets worse in adults, though your provider may want follow-up X-rays if you are young or your symptoms change.
Can spondylolisthesis be reversed?
The bone does not slide back into place, and the pain it causes still responds well to treatment. Strengthening the muscles that support the segment and avoiding the positions that load it changes how you feel day to day, even though the X-ray stays the same.
What activities should I avoid with spondylolisthesis?
Repeated arching of the lower back is the main one. That rules out gymnastics-style backbends, heavy overhead pressing with an arched back, and high-impact sports during a flare. Long periods of standing tend to aggravate it, while walking and swimming are usually fine.
Does spondylolisthesis get worse with age?
Adult slips tend to stay put. The wear-and-tear type can progress slowly as the disc and joints keep wearing. A follow-up X-ray every few years is reasonable when the slip is causing symptoms.
Can I still exercise with a slipped vertebra?
Yes, and exercise is part of the treatment. Core strengthening, forward-bending movement, and low-impact cardio all help. The exercises to skip are the ones that push your lower back into an arch, and which ones those are depends on your level and grade.
Can a car accident cause spondylolisthesis?
Sometimes, if the impact fractures the bone holding the vertebra in place. More often, an accident reveals or aggravates a slip that was already there. A standing X-ray and a neurological exam after the accident show whether the slip has changed and whether the pain is coming from the slip or from the injury around it.